Atypical Moles and Melanoma Risk: Clinical Insights from Oncologic Research
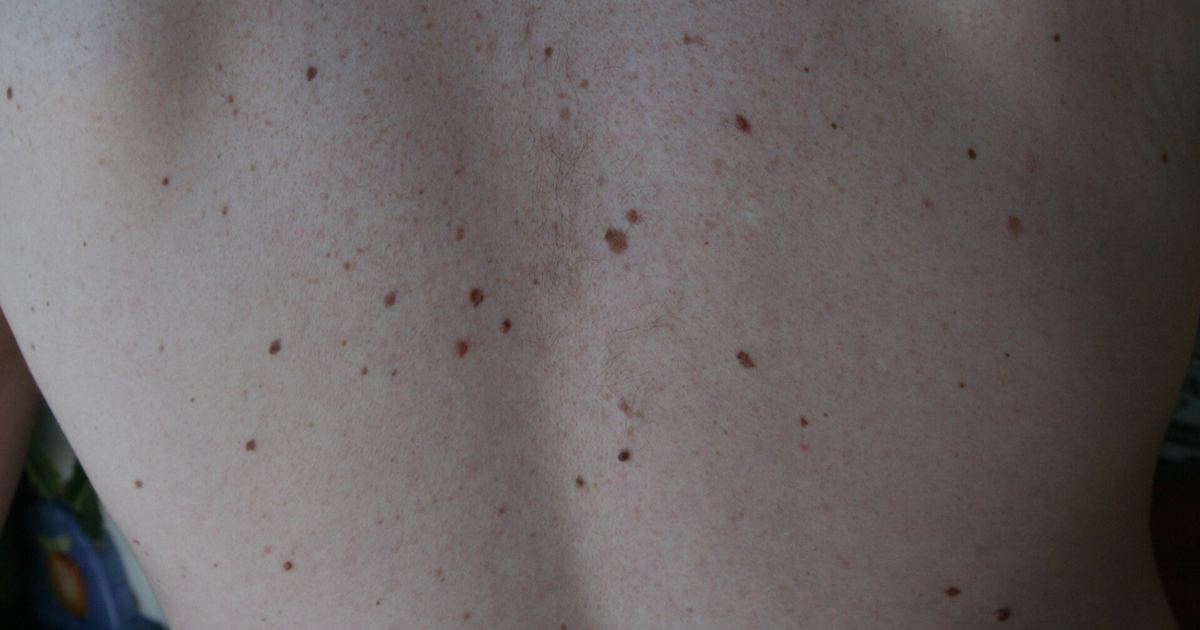
Understanding how physical skin markers relate to skin cancer risk is a core component of preventive dermatology. A landmark 1996 review article titled Dysplastic nevi and other risk markers for melanoma, published in Seminars in oncology, evaluated how specific physical traits and clinical histories indicate heightened vulnerability to melanoma. For readers researching skin health, navigating information about moles, or learning about skin changes, understanding the medical evidence behind risk markers provides crucial context on how clinicians identify individuals at high risk.
What Did the 1996 Review Set Out to Investigate?
The 1996 review synthesized clinical evidence on cancer risk markers. In oncology, risk markers are defined as genetic or behavioral attributes that demonstrate a statistical association with an increased incidence of cancer. The authors explained that medical researchers identify and assess these markers primarily through two distinct epidemiological study designs:
- Case-control studies: Research comparing individuals diagnosed with melanoma against individuals without the disease to identify historical or physical differences.
- Cohort studies: Investigations in which groups of individuals possessing particular physical or behavioral attributes are tracked over time, allowing researchers to determine cancer risk through direct observation.
Both methodological frameworks have contributed significantly to mapping the major risk factors associated with malignant melanoma.
Why Are Dysplastic Nevi Identified as Primary Clinical Indicators?
According to the review in Seminars in oncology, the presence of dysplastic nevi (often referred to as atypical moles) represents the single most important risk marker for melanoma. Dysplastic nevi are regarded within oncology as intermediate lesions of tumor progression. Observational data indicated that approximately 30% of melanomas arise in direct association with a precursor nevus, and that precursor lesion is most commonly dysplastic.
However, the study emphasized a critical biological paradox: although they are closely linked to melanoma risk, dysplastic nevi are vastly more numerous on human skin than actual melanomas. As a consequence, the vast majority of dysplastic nevi remain completely stable lesions that never progress into malignancy. Recognizing them serves as a tool for estimating a person's overall statistical risk rather than implying that every atypical spot will become cancerous.
What Other Factors Compound an Individual's Vulnerability?
The presence of atypical nevi rarely exists in clinical isolation. The paper highlighted additional major categories of melanoma risk factors that clinicians evaluate in combination:
- Family and personal history: Having a personal history of melanoma or a family history of the disease significantly increases baseline risk.
- Indicators of acute and chronic sun exposure: Physical signs showing accumulated ultraviolet exposure—specifically freckles, actinic skin damage, and a documented history of sunburn—serve as key clinical risk markers.
When clinicians evaluate these combined markers in oncological patients and their first-degree relatives, they can identify specific cohorts whose melanoma risk ranges from several-fold to more than 100-fold greater than the risk seen in random members of the general population. Comparing common moles vs dysplastic nevi demonstrates why medical professionals closely audit these visible skin characteristics.
What Are the Methodological Boundaries and Limits of This Study?
When interpreting these findings, it is essential to consider the design and inherent limits of the paper:
- Study design: This was a narrative review paper published in 1996, relying on research support from the U.S. Government and Public Health Service, rather than a prospective clinical trial.
- Observational data: The conclusions were drawn from observational cohort and case-control studies. These study types demonstrate statistical associations between markers and cancer incidence, but they do not isolate single causative biological triggers.
- Risk marker vs. disease: A risk marker indicates statistical vulnerability across populations; it is not a diagnosis. Because most dysplastic nevi remain stable, their presence cannot definitively predict whether an individual will develop melanoma.
Because individuals researching skin pigmentation or considering unapproved compounds online may misunderstand how lesions evolve, examining evidence in melanoma and mole research underscores the importance of relying on qualified medical evaluations rather than self-diagnosis.
Why Is Risk Stratification Valuable for Early Diagnosis?
The primary clinical value of recognizing atypical moles and exposure markers lies in targeted surveillance. The authors noted that identifying people whose risk is several-fold to over 100-fold higher enables focused early diagnostic efforts. When high-risk patients and their first-degree relatives receive regular clinical surveillance, emerging melanomas can be recognized in their early, curable stages, preventing the progression of deep, life-threatening malignancies.
Sources
Dysplastic nevi and other risk markers for melanoma. - PubMed
Published October 30, 2026. Sources are linked in the text. See our Medical Disclaimer.